Other inflammatory conditions such as calcium hydroxyapatite deposition disease (HADD) may affect the shoulder (Figure 12-26).
The supraspinatus is the superior rotator cuff muscle. Results The teres minor is an external rotator and adductor of the arm. Considering the glenohumeral joint not a weight-bearing joint, de novo osteoarthritis is less common, and posttraumatic versus calcium pyrophosphate deposition disease (CPPD) should be considered in cases of severe osteoarthritis of the shoulder. It consists of four joints: sternoclavicular, acromioclavicular, scapulothoracic, and glenohumeral. Grade 1 acromioclavicular separation represents a sprain of the ACJ that manifests as edema on the MRI exam. Normal outpouchings of the joint capsule include the biceps tendon sheath, axillary recess, rotator interval, and subscapularis recess. These need to be watched and treated as appropriate The MRI is a sophisticated imaging technique that stands out with its superior ability to discriminate soft tissue structures. The end-stage of the process is arthritis and joint destruction. Coronal oblique spin echo T2-weighted image shows fluid signal (black arrow) in the insertion of the supraspinatus without retraction of tendon indicating full-thickness tear. T2 star gradient recall echo images are employed in the assessment of the labrum and for detection of substances that produce susceptibility effects such as calcium hydroxyapatite or loose surgical hardware. For those situations, I have a video on how to read a shoulder MRI, provided at the bottom of this page. The damage is progressive and eventually leads to a tear. On average, theoutcomes forshoulder replacement patients are not nearly as good as hip or knee replacements (3). WebWhat can white spots on spine in mri scan indicate? For example, a 2 oclock lesion is localized to the anterior superior quadrant. Axial MRI shows paralabral cysts (black arrow) associated with a superior labral anterior to posterior tear. Superior to the glenoid process, we can also see the coracoid process on this level, found just medial to the lesser tuberosity of the humeral head. Figure 1. Note bright signal fluid is replacing the torn tendon. T2 hyperintensities (lesions). J. Manaster, Zehava Sadka Rosenberg (2016). The glenohumeral joint is a synovial joint, formed by the glenoid fossa of the scapula and the head of the humerus, while the acromioclavicular joint connects the acromion and the lateral part of the clavicle. __________________________________________________, (1) Harada Y, Kokubu T, Mifune Y, et al. NOTE: This blog post provides general information to help the reader better understand regenerative medicine, musculoskeletal health, and related subjects. A nonosseous Bankart spares the bony glenoid rim. White spots were in several places in my head and down the side of my neck. The inferior glenohumeral ligament is shown along the inferior aspect of the glenohumeral joint. Study of the scapular muscle latency and deactivation time in people with and without shoulder impingement. This structure should not be resected if there is an irreparable rotator cuff tear, as it resists anterior superior humeral head escape. Copyright Regenexx 2023. This form of impingement is associated with the complex of lesions classified by the term microinstability. These include the superior labral anterior cuff (SLAC) tear lesion. Complications of direct arthrography are rare.
On the superior aspect of the humeral head, we can visualize the lesser tuberosity medially, and the greater tuberosity laterally. Impingement is a clinical diagnosis that may be supported with radiologic findings.3. When looking at the bones, we should evaluate their intensity, shape and contours and look out for any osteophytes or fractures. I did.
The shoulder is a large and complicated joint that we use on a daily basis. Chronic repetitive trauma of the superiorly subluxed humeral head may lead to remodeling of the acromion and eventual collapse of the humeral head (rotator cuff arthropathy). To get a deeper understanding of the fundamentals of the MRI, have a look at our article below to learn more information. Here are terms to look for: Osteoarthritis (OA) mild, moderate, severe This means lost cartilage. Quadrilateral space compression is associated with axillary nerve entrapment and deltoid/teres minor denervation. Patients with anterior superior instability due to a biceps pulley injury are predisposed to secondary subcoracoid impingement due to abnormal anterior superior translation of the humeral head. Richard Ramos answered. The coracoid process is an anterior bony extension arising from the anterolateral aspect of the scapula. X-ray and CT images can be considered to be a map of density of tissues in the body; white areas on X-ray and CT images represent high density structures. In the absence of a joint effusion, fluid or synovitis in the biceps sheath is suggestive of biceps tenosynovitis (Figure 12-24). In the late cocking/early acceleration phase of the throwing mechanism, the arm is in maximal ABER. These lesions are described respectively as Bankart/Bankart variant and HillSachs lesions (Figures 12-14 to 12-16). Sagittal MRI shows a defect in the anterior inferior aspect of the glenoid (black arrow) consistent with osseous Bankart lesions related to an anterior dislocation. What kind of symptoms are you having? Sagittal MRI shows a hook of the anterior lateral acromion (black arrow) consistent with a type 3 acromion. Posterior superior internal impingement is often seen in patients who engage in repetitive overhead athletic activities. 88 clinic locations offering non-surgical Regenexx solutions for musculoskeletal pain. Note a small articular cartilage defect representing GLAD lesion. They never did. One or more of the four areas above will be commented on if theres an abnormality. This condition may be secondary to traumatic causes with disruption of the blood supply. Coronal oblique MRI shows a disruption of the articular surface of the supraspinatus near its insertion (black arrow). Fundamentals of diagnostic radiology (4th edition).
MRI, or magnetic resonance imaging, reveals these spots with greater intensity because they have increased water content compared to normal, higher fat content, myelinated tissue in the brain. It consists of the coracoid process, coracoacromial ligament, and acromion.
Results Anterior superior internal impingement is an uncommon diagnosis due to biceps pulley injury. This acromial morphology has been associated with subacromial impingement. Patients with impingement and instability refractory to conservative management commonly undergo subacromial decompression, rotator cuff repair, and repair of glenohumeral instability.1316. I'm curious now, is this cancer? A few general comments about conventional and arthrographic MRI protocols will be made. The joint capsule is a static stabilizer of the glenohumeral joint. As an example, below is an overview of the shoulder on an axial PD image at the level of the glenoid cavity. In simple terms, MRI images can be considered as a map of proton energy within tissues of the body.
Figure 2. White spots on your MRI can show up even if you have no symptoms of illness. Also realize that arthritis maybe caused by instability in the joint, due to loose ligaments. Providers listed on the Regenexx website are for informational purposes only and are not a recommendation from Regenexx for a specific provider or a guarantee of the outcome of any treatment you receive. There are two main causes of rotator cuff tears. Montesinos, P., Guedez, M., Aguilella, L., Cerezal, L., & Llopis, E. (2015). The damage is progressive and eventually leads to a tear. Figure 12-10. This makes it the most mobile joint in the body. Acromion Glenoid Head of Humerus Shaft of Humerus Rotator cuff muscle Deltoid muscle Axial MRI shows a chondral cap of an osteochondroma (black arrow) arising from the humeral shaft. Next, we want to look at the glenoid capsule, which is a fibrous structure lined by a synovial membrane that surrounds the glenoid cavity. Biceps tendinopathy may be treated with tenodesis (resection and reattachment of the biceps to the bicipital groove) or tenotomy (resection of the tendon allowing release of tendon with distal retraction). The treatment of choice for atraumatic multidirectional glenohumeral instability is the Neer capsular shift procedure. Depends: Spine MRI usually is done based on the region of the spine that is being imaged. Microvascular disease. Dead arm is a condition characterized by the sudden loss of the ability to throw a fastball in the elite overhead athlete.9,10 The event immediately preceding this condition is a posterior SLAP 2 tear. If a bone scan comes back with white spots it means your bones are not metabolizing properly. Simply put, the MRI triggers the protons in the tissues to produce a signal that is measured and transformed into a gray-scale image. The MRI allows accurate assessment of any pathologic changes of the structures of the shoulder, including the glenoid labrum, the humeral head, the articular cartilage, and the rotator cuff. An incision is made in the anterior joint capsule. The shoulder is a large and complicated joint that we use on a daily basis. Do not use this information to diagnose or treat a health problem or disease without consulting with a qualified healthcare provider. Worst case scenario, Multiple Sclerosis. Holes are drilled through the bony glenoid. Acromion Glenoid Head of Humerus Shaft of Humerus Rotator cuff muscle Deltoid muscle Posterior superior impingement develops due to repetitive stress in overhead activities.
Some will cause the edge of the bone to push out, but rarely do the tumors extend past the bone and into the surrounding soft tissue. The shape of the undersurface of the acromion may be classified according to morphology: type 1 (Figure 12-4), flat undersurface; type 2, concave undersurface (Figure 12-5); type 3, acromion, anterior lateral hook (Figure 12-6). In the spinal cord.Multiple sclerosis, tumor, On occasion, a mass may be encountered by the interpreting radiologist, who must then make appropriate recommendations to the referring clinician. The shoulder joint is a joint that connects the upper limb to the axial skeleton. Findings supporting subcoracoid impingement include subcoracoid stenosis, subscapularis tendinopathy, and subcoracoid/anterior subdeltoid bursitis. MRI images are different. Gordana Sendi MD Bhuskute, N. and Guthrie, A., 2011. It all depends on where they are located. Subacromial/subdeltoid bursitis. Usually, the images are taken in three planes; coronal oblique, sagittal oblique and axial plane. These include: Attrition This is a wearing down of the tendons over a period of time from regular usage of the shoulder. Injuries of the posterior inferior glenoid associated with posterior dislocation are called reverse Bankart lesions (Figure 12-17). An os acromiale (Figure 12-7) is an unfused acromial ossification center. Instability usually responds well to ligament tightening injections. MR arthrography is employed for the detection of subtle rotator cuff tears or labral pathology in patients with a negative conventional MRI, the assessment of the postoperative shoulder, and the demonstration of communication between the joint and extra-articular pathology such as a paralabral cyst. Osteophytes This means bone spurs.
Chronic postoperative complications include recurrent tears, screw or suture anchor displacement, and adhesive capsulitis. Read more. The shoulder in a conventional MRI exam is acquired in partial external rotation in the axial, coronal and sagittal planes. The decision to repair a cuff tear may be based on prognostic imaging findings, symptoms, and functional expectations of the patient. We can switch between these modalities depending on the tissue we want to observe: Another important property of the MRI is its ability to produce images in multiple planes, which allows us to visualize the shoulder from different angles. The glenoid labrum is best seen in the axial plane, appearing on the anterior and posterior rim of the glenoid as two triangular-shaped low signal structures on all pulse sequences. WebOne of the most common findings on a shoulder MRI is a rotator cuff tear. The images produced by MRI The white arrow points to the rotator cuff tendon, thick and entirely grey, read as tendinosis. Sequences may be tailored according to clinical indication. Take this quiz. A variety of anterior labroligamentous complex/Bankart variant injuries have been described (Figure 12-18).8 The anterior labroligamentous periosteal sleeve avulsion (ALPSA) lesion is characterized by an intact medial scapular periosteum against which the torn labroligamentous complex migrates. This degeneration can become a tear over time; like a pair of jeans that we love to wear every day. In about 25 to 40% of cases, an X-ray will show calcifications (white spots) inside the tumor. These are the lubricating sacs around the shoulder that allow normal motion of tendons as they cross each other and bony areas. Want to test your knowledge before reading into the details? Although acromioclavicular osteoarthritis is common, subchondral edema is associated with symptomatic cases presenting as anterior superior pain. Dimitrios Mytilinaios MD, PhD This can indicate a bone tumor, a fracture, infection, metabolic disorders or cancer that has metastasized to the bone from a tumor that started somewhere else, according to the Mayo Clinic 1. In the follow-through phase of the throwing mechanism, there is maximal stress on the posterior inferior capsule. A complete tear (Figures 12-12 and 12-13) is total discontinuity of the tendon that is often associated with superior migration of the humeral head. The shoulder is a large and complicated joint that we use on a daily basis. These can also be followed by fluid in the subacromial space or retraction of the rotator cuff tendon. The inferior glenohumeral ligament consists of anterior and posterior bands with an intervening axillary pouch, the most dependent portion of the joint. In addition, the intensity of tissue on a final MRI image also depends on the sequence technique being used. Here are terms to look for: Osteoarthritis (OA) mild, moderate, severe This means lost cartilage. At this level, the tendon of the long head of biceps brachii is located in the bicipital groove, while the tendon of the short head is found at the tip of the coracoid process. Figure 12-5. Try to get your doctor on the phone as soon as possible. An MRI report can call white matter changes a few different things, including: Cerebral or subcortical white matter disease or lesions. Calcium deposition can be seen in the rotator cuff, bursae, or in the tissues around the joint. Depends: Spine MRI usually is done based on the region of the spine that is being imaged. An osseous Bankart lesion involves the anterior band of the inferior glenohumeral ligament, the anterior inferior labrum, the adjacent medial scapular periosteum, and the underlying osseous glenoid rim. Advanced osteoarthritis. Grade 5 separations ACJ and CC ligament disruption along with tears of the deltoid and trapezius associated with superior displacement of the clavicle. Thank you in advance for your help. Learning anatomy is a massive undertaking, and we're here to help you pass with flying colours. Type 1 acromion. Calcific tendinitis. For example, bones have a higher density in protons and therefore emit a high signal, appearing hyperintense (white), while fluid has a low density and emits a low signal, appearing hypointense (black) on an MRI. WebOn X-ray images, they are often surrounded by a thin rim of white bone. WebThere were white spots like circles on my upper arm. Davis Company. As we scroll further downwards, we can follow the muscle as it extends laterally into the supraspinatus tendon, which is seen as a low intensity structure that arches over the humeral head to attach on the greater tuberosity of the humerus. As impingement evolves, tendinosis develops in the bursal aspect of the supraspinatus.
Check out our study units below to solidify your knowledge of the glenohumeral and acromioclavicular joints with our video tutorials, quizzes and labeled diagrams! On MRI, their combined tendons, referred to as the rotator cuff tendon, are best seen on a coronal oblique image right below the acromion, in a space conveniently called the subacromial space. We will first look at the static stabilizers, that include the glenoid labrum, fibrous capsule, glenohumeral and coracohumeral ligaments. However, once you have the Shoulder MRI Reportin hand, the next step is usually a series of Google searches in an attempt to decipher all of the medical jargon and anatomical references. In addition, any injection into this area of the shoulder should only be performed with ultrasound guidance, so stay clear of doctors who perform blind and/or unguided injections, as they may be injecting into the wrong spot. doi:10.1055/s-0035-1549316. Coracoacromial ligament resection is part of the subacromial decompression operation. Variations in labral attachment and congenital deficiency may be confused with pathology. The superior, middle and inferior glenohumeral ligaments are thickenings of the glenoid capsule that attach onto the anteroinferior margin of the glenoid labrum and reinforce the capsular tissue. Note the white arrow is pointing to torn and retracted supraspinatus tendon. Figure 1. WebOn X-ray images, they are often surrounded by a thin rim of white bone. X-ray and CT images can be considered to be a map of density of tissues in the body; white areas on X-ray and CT images represent high density structures. Figure 12-27. The sagittal plane is acquired parallel to the glenoid articular surface and perpendicular to the long axis of the supraspinatus. The coracohumeral ligament is a triangular ligament that originates on the lateral horizontal portion of the coracoid process and fans out to insert in the lesser and greater tuberosities of the humerus, as well as the biceps sheath. Figure 12-29.
It is not a substitute for professional medical advice. MRI can assist in identifying and grading these injuries.11 Six grades of acromioclavicular separation are described under the Rockwood classification.
Superior labrum anterior and posterior lesions of the shoulder: incidence rates, complications, and outcomes as reported by American Board of Orthopedic Surgery. Different tissues have different density of protons, hence the signal varies in intensity, allowing the MRI to discriminate one tissue from another. T1-weighted sagittal image optimally depicts advanced muscle atrophy and fatty degeneration around the shoulder including the supraspinatus (black arrow). Progression of the process leads to partial tears or discontinuity of the tendon and eventually full-thickness rotator cuff tears (Figures 12-9 to 12-11). Coronal oblique MRI shows findings of avascular necrosis with subchondral collapse of the medial aspect of the head (black arrow). These include the sublabral recess, sublabral foramen, and the Buford complex. This finding has been associated with subacromial impingement. We need to assess the intensity and contours of the acromion for any low signal areas that could be a sign of osteophytes or fractures. Underlying subacromial/subdeltoid bursitis and rotator cuff tendinopathy are also demonstrated. Patients with shoulder impingement typically present with activity-related diffuse pain in the region of the deltoid muscle. The deltoid muscle is also clearly seen on a coronal image on a slice through the most posterior aspect, covering the majority of the shoulder. Injury Acute trauma to the shoulder leads to a tear in the tendon. Figure 12-22. Hi everybody. If needed, we can use a sagittal image to visualize the glenohumeral ligaments separately. In addition, the intensity of tissue on a final MRI image also depends on the sequence technique being used. All rights reserved. The morphology of the tear may be described as crescentic (mild medial retraction), U-shaped (massive tear involving the anterior posterior dimension of the cuff), and L-shaped (massive tear with preservation of the anterior cuff). Coronal oblique MRI shows tears of the coracoclavicular ligaments (white arrow) and disruption and malalignment of the acromioclavicular joint (black arrow). They originate around the scapula and attach to the humeral head. We will now proceed to give a more in depth overview of the individual bones as well as the surrounding soft tissue structures of the shoulder, to provide a simple guideline on how to evaluate these structures on the MRI. There were white spots like circles on my upper arm. It is associated with lesions of the superior labrum, posterior supraspinatus, and superior infraspinatus. There is a bursal surface tear of the supraspinatus near the myotendinous junction (white arrow). In vivo effects of single intra-articular injection of 0.5% bupivacaine on articular cartilage. These include the rotator cuff and the surrounding muscles. WebWhite spots may be seen in several benign conditions such as migraine headache, however if in association with hypertension and diabetes, they may be representative of "mini strokes" which are often "silent" without symptoms. This entity is referred to as the hidden lesion due to the difficulty of making the diagnosis based on clinical or arthroscopic findings. Subacromial and subcoracoid external impingement will be discussed. This is a normal variant called os acromiale and it should not be mistaken for a fracture. Sagittal MRI shows concave undersurface of the acromion consistent with type 2 acromion (black arrow). 2011;93(21):1953-1960. doi:10.2106/JBJS.K.00488, (6) Phadke V, Ludewig PM. The infraspinatus and teres minor also attach to the greater tuberosity, superiorly and inferiorly, respectively. Home Blog Whats a Normal vs. Abnormal Shoulder MRI? Grade 6 separation differs from grade 5 injuries as the clavicle is inferiorly displaced. The infraspinatus arises from the infraspinous fossa. MRI images are different. The images produced by MRI It internally rotates and adducts the arm. The AC joint is the joint between the collar bone and the shoulder blade. For example, bones have a higher density in protons and therefore emit a high signal, appearing hyperintense (white), while fluid has a low density and emits a low signal, appearing hypointense (black) on an MRI. The biceps pulley stabilizes the long head of the biceps tendon that is a primary restraint to anterior superior subluxation of the humeral head.
Tenosynovitis.
The rotator cuff muscles originate on the scapula with their tendons converging towards their respective attachment sites. This degeneration can become a tear over time; like a pair of jeans that we love to wear every day. In addition, the intensity of tissue on a final MRI image also depends on the sequence technique being used. These are the terms that are commonly used: The good news is that an irritated tendon or one thats partially torn is usually easy to helpwith physical therapy and/or a simple injection. Subchondral cysts and osteophytes are demonstrated in this case of severe osteoarthritis of the glenohumeral joint. Chronic muscle atrophy. In certain cases, referral to an orthopedic surgeon specializing in neoplasms is appropriate. Sagittal MRI shows there is a gap that involves the entire supraspinatus tendon (black arrow) in this patient who is status post rotator cuff repair. Figure 12-17. In simple terms, MRI images can be considered as a map of proton energy within tissues of the body. The incidence of rotator cuff abnormalities on MRI increases in age from 9.7% at age 20 and under to 67% over 80 (1). Copyright 2000-2022 Cancer Survivors Network.
A tear can be a partial tear or a full tear. On a slice through the center of the glenohumeral joint, we see the contours of the proximal shaft, the neck, and the head of the humerus. Dose- and time-dependent effects of triamcinolone acetonide on human rotator cuff-derived cells. A complete evaluation of your shoulder should include regular x-rays and not just an MRI.
Figure 12-14. WebWhite spots may be seen in several benign conditions such as migraine headache, however if in association with hypertension and diabetes, they may be representative of "mini strokes" which are often "silent" without symptoms. Two characteristic forms of microtraumatic instability will be discussed. Figure 2. The supraspinatus and infraspinatus are innervated by the suprascapular nerve that passes through the suprascapular and spinoglenoid notches, common sites of entrapment. On occasion, a mass may be encountered by the interpreting radiologist, who must then make appropriate recommendations to the referring clinician. The subscapularis is innervated by the subscapular nerve. WebOn MRI images white = high signal. *DISCLAIMER: Like all medical procedures, Regenexx Procedures have a success and failure rate. Musculoskeletal imaging handbook: a guide for primary practitioners.
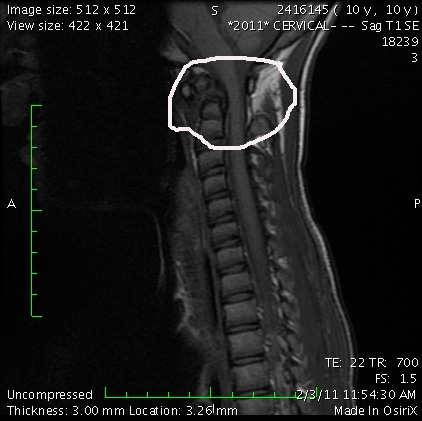 On average, theoutcomes forshoulder replacement patients are not nearly as good as hip or knee replacements (3). WebWhat can white spots on spine in mri scan indicate? For example, a 2 oclock lesion is localized to the anterior superior quadrant. Axial MRI shows paralabral cysts (black arrow) associated with a superior labral anterior to posterior tear. Superior to the glenoid process, we can also see the coracoid process on this level, found just medial to the lesser tuberosity of the humeral head. Figure 1. Note bright signal fluid is replacing the torn tendon. T2 hyperintensities (lesions). J. Manaster, Zehava Sadka Rosenberg (2016). The glenohumeral joint is a synovial joint, formed by the glenoid fossa of the scapula and the head of the humerus, while the acromioclavicular joint connects the acromion and the lateral part of the clavicle. __________________________________________________, (1) Harada Y, Kokubu T, Mifune Y, et al. NOTE: This blog post provides general information to help the reader better understand regenerative medicine, musculoskeletal health, and related subjects. A nonosseous Bankart spares the bony glenoid rim. White spots were in several places in my head and down the side of my neck. The inferior glenohumeral ligament is shown along the inferior aspect of the glenohumeral joint.
 Study of the scapular muscle latency and deactivation time in people with and without shoulder impingement. This structure should not be resected if there is an irreparable rotator cuff tear, as it resists anterior superior humeral head escape. Copyright Regenexx 2023. This form of impingement is associated with the complex of lesions classified by the term microinstability. These include the superior labral anterior cuff (SLAC) tear lesion. Complications of direct arthrography are rare.