high estrogen levels before frozen embryo transfer
Estrogens may be administered orally, vaginally and parentally (transdermal route) and both natural as well as synthetic estrogens may be used (Scott et al., 1991b). The physiological and clinical importance of the pre-ovulatory progesterone elevation is yet to be determined, but is likely to contribute to the induction of the WOI in a NC.
Although FET is increasingly used for multiple indications, the optimal preparation protocol is yet to be determined. Guan Y, Fan H, Styer AK, Xiao Z, Li Z, Zhang J, Sun L, Wang X, Zhang Z. Haddad G, Saguan DA, Maxwell R, Thomas MA. 226 0 obj
<>/Encrypt 198 0 R/Filter/FlateDecode/ID[<529F281E282F8C46A38C2601D988F8F7><97AAD02F18A75344BA2A92AB847009A8>]/Index[197 58]/Info 196 0 R/Length 117/Prev 119848/Root 199 0 R/Size 255/Type/XRef/W[1 2 1]>>stream
The reason is that high estrogen levels can lead to the development of ovarian In most cases, the transfer occurs in the following menstrual cycle the next month. Meanwhile, even in the general population, delayed endometrial development has been described in up to 25% of the population (Murray et al., 2004) and an increase in pregnancy rates associated with specific histological endometrial dating patterns and corresponding adjustments in progesterone exposure has been shown (Gomaa et al., 2015). 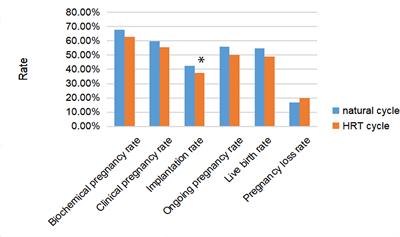

 However, it seems that such an extended period may be unnecessary and that 57 days may suffice for adequate endometrial proliferation (Navot et al., 1986). A recent double-blinded placebo-controlled RCT demonstrated non-inferiority and a similar safety profile for the oral administration of dydrogesterone in fresh cycles (Tournaye et al., 2017). This should be the preferred terminology as it emphasizes the synchronicity between endometrium and embryo. WebAlthough estrogen levels in normal natural cycles reach 300400 pg/ml before ovulation, a study on donor cycles revealed that the E 2 requirement for embryo implantation is low The number of high quality randomized controlled trials (RCTs) is scarce and, hence, the evidence for the best protocol for FET is poor. Call now: (608) 824-6160. The results of this trial are also in contradiction with those of subsequent systematic reviews and meta-analyses, which failed to demonstrate any benefit in terms of clinical pregnancy and cancellation rates (Ghobara and Vandekerckhove, 2008; Glujovsky et al., 2010). High levels of E 2 ( 100 nM) during in vitro culture are deleterious at the two-cell stage [ 13, 24 ], but E 2 supplementation at 8 nM during the peri-implantation period successfully facilitates in vitro attachment and outgrowth of both human and mouse embryos [ 25, 26, 27, 28 ].
They can later be thawed as well as transferred via a frozen embryo transfer cycle, or FET. Once the proliferation of the endometrium with the administration of estrogens is considered sufficient, progesterone is initiated to promote the final phase of endometrial preparation prior to embryo transfer. For intra-uterine insemination, it has been shown that pregnancy rates are higher when it was performed 3642 h after hCG trigger, but 1824 h after spontaneous LH surge (Fuh et al., 1997; Robb et al., 2004).  https://alexroblesmd.com/wp-content/cache/breeze-minification/js/breeze_d8b9ac1cac0e674c1a0b0961093927ba.js, https://alexroblesmd.com/wp-content/cache/breeze-minification/js/breeze_e709f6277bbec007e5a021ac9cdc419b.js, https://alexroblesmd.com/wp-content/cache/breeze-minification/js/breeze_d6638419dc0ffa7ebd981022572d700a.js, https://alexroblesmd.com/wp-content/cache/breeze-minification/js/breeze_b410f7096d4a966b622520512b7f5e7d.js. Serum progesterone assessments may be used to detect escape ovulation, an event which can be encountered in 1.97.4% of HRT FET cycles without pituitary suppression (Dal Prato et al., 2002; van de Vijver et al., 2014). Dr. Alex Robles is a Spanish-speaking Latino-American Reproductive Endocrinologist and Infertility specialist in New York City, and a board-certified OBGYN. But this doesnt seem to hold true for the general population. A difference in the timing of FET in true versus modified NC could be considered, as ovulation occurs 3648 h after hCG administration but varies from 24 to 56 h after a spontaneous LH surge (Kosmas et al., 2007). One could draw the parallel to FET and transfer 1-day earlier when a spontaneous LH surge is detected in the serum compared to when ovulation is triggered with hCG. In case the estrogen levels drop unexpectedly before egg retrieval, this can be a bad sign.
hormonal substitution with estrogen (E2) and progesterone) have proven to be effective to prepare However, an impact has been described of the method of freezing on post-thaw embryo development and metabolism (Balaban et al., 2008; Cercas et al., 2012) and further research into the potential clinical effects of such differences might optimize embryo-endometrial synchrony. Vitrification can modify embryo cleavage stage after warming.
The more follicles you have, the more estrogen is produced, and the faster your E2 level will rise. [] The endometrial thickness is related to endometrial receptivity as the most Scott R, Navot D, Liu HC, Rosenwaks Z. Scott RT, Ross B, Anderson C, Archer DF.
Roque M, Valle M, Guimares F, Sampaio M, Geber S. Ruiz-Alonso M, Blesa D, Daz-Gimeno P, Gmez E, Fernndez-Snchez M, Carranza F, Carrera J, Vilella F, Pellicer A, Simn C. Sathanandan M, Macnamee MC, Rainsbury P, Wick K, Brinsden P, Edwards RG. WebIt is possible to get pregnant if you are living with high estrogen levels, however, there is an increased likelihood of fertility issues in those who are living with estrogen Second, it is possible that in the prematurely interrupted study there could have been a higher embryo-endometrial asynchrony in the modified NC study group as FET timing was the same for both arms, despite known differences in the timing of spontaneous versus triggered ovulation (Kosmas et al., 2007). The actual value of your estradiol (E2) during IVF isnt as important as the overall trend and the number of ovarian follicles you have growing. For example, an E2 level of 1000 might yield 3-5 mature oocytes at the egg retrieval (as not all follicles yield eggs). If fertility issues have prevented you from having children, consider UW Health's Generations team of experts. a Day 5 embryo on hCG + 7). What the normal range for estradiol levels are in an IVF cycle, What to expect the level to be on any given day, Poor responders: Patients in the bottom 10th percentile for estrogen levels, Normal responders: Patients in the 50th percentile for estrogen levels, High responders: Patients in the 90th percentile for estrogen levels, It thickens the uterine lining in preparation for embryo implantation, It helps fertility doctors monitor your response to IVF stimulation and predict the number of oocytes you might get at the oocyte retrieval, It plays an important role in endometrial receptivity and pregnancy maintenance. Fatemi HM, Kyrou D, Bourgain C, Van den Abbeel E, Griesinger G, Devroey P. Franasiak JM, Ruiz-Alonso M, Scott RT, Simn C. Frydman R, Testart J, Fernandez H, Arvis P, Belaisch JC. Furthermore, the definition of what constitutes an LH surge is not unanimous. Estrogen can be low during an IVF cycle for one of two reasons. A meta-analysis has demonstrated that, following a fresh embryo transfer, progesterone can be discontinued once a positive pregnancy test is detected (Liu et al., 2012). Progesterone rises slightly to 13 ng/ml even 12 h to 3 days prior to ovulation, due to the LH-stimulated production by the peripheral granulosa cells (Hoff et al., 1983), with a steep increase in production following ovulation (310 ng/ml) due to production by the corpus luteum. Are There Other Side Effects Of High Estrogen Levels? Estrogen. The starting point to assess embryo-endometrial synchronization is the ovulation of the dominant follicle, which in a NC can either be triggered exogenously (i.e. WebWhen estrogen is too high or too low you may get menstrual cycle changes, dry skin, hot flashes, trouble sleeping, night sweats, vaginal thinning and dryness, low sex drive, mood Advertisement intended for healthcare professionals, Universitair Ziekenhuis Brussel, Vrije Universiteit Brussel. Prenatal, vitamin d because my level was a little low. WebAn estrogen level above 3,500 pg/mL is considered high and a risk factor for adverse effects. A previous retrospective analysis has shown a higher miscarriage rate for HRT compared to NC FET, although this could be related to the higher proportion of polycystic ovary syndrome patients in the HRT group (Toms et al., 2012). Overall, the moment to start LPS in a NC FET is unclear although one may postulate that immediately after the LH surge or hCG trigger may be too soon and affect the window of implantation (WOI). Frozen embryo transfers can occur years after egg retrieval and fertilization.
A Cochrane Database Review concluded that starting progesterone at a time equivalent to the day of or the day after oocyte retrieval (OR) results in a significantly higher pregnancy rate than if progesterone is initiated a day earlier than the day equivalent to OR (Glujovsky et al., 2010). When using the LH surge to plan embryo transfer one must take into account that the LH surge can occur over a period of 30 h (Acosta et al., 2000). Literature on the topic was retrieved in PubMed and references from relevant articles were investigated until June 2017. Use of the natural cycle and vitrification thawed blastocyst transfer results in better in-vitro fertilization outcomes: cycle regimens of vitrification thawed blastocyst transfer, Outcomes of vitrified early cleavage-stage and blastocyst-stage embryos in a cryopreservation program: evaluation of 3,150 warming cycles, Histological dating of timed endometrial biopsy tissue is not related to fertility status. The study appears in the August issue of Fertility and Sterility. Sorry you're going through this, is your RE concerned? Written by Hannah Kingston. Using hormones such as estradiol may Although I am a physician by profession, I am not YOUR physician. WebHi, I just finished my first IVF. Loutradi KE, Kolibianakis EM, Venetis CA, Papanikolaou EG, Pados G, Bontis I, Tarlatzis BC.
]+7\M*2{>N )Xt$W8{[0c*3AsxFldhGQe +t}xFYSi*|%HI?6?0\:L~N~$ ac%oXY{\68*-G/
There is limited information available regarding the need for endocrine monitoring during HRT. The optimal duration of exposure to progesterone prior to embryo transfer has remained an elusive topic since the start of ART (Nawroth and Ludwig, 2005). No consensus has been reached yet on when to stop progesterone administration following a positive pregnancy test in HRT FET. Jin R, Tong X, Wu L, Luo L, Luan H, Zhou G, Johansson L, Liu Y. Jordan J, Craig K, Clifton DK, Soules MR. Kaser DJ, Ginsburg ES, Missmer SA, Correia KF, Racowsky C. Kasius A, Smit JG, Torrance HL, Eijkemans MJC, Mol BW, Opmeer BC, Broekmans FJM. apOj-&FPKg|` V$
The administration route and dose also needs to be taken into account when performing such endocrine monitoring. injection: cycle and pregnancy outcomes in IVF patients receiving vitrified blastocysts, Age and uterine receptiveness: predicting the outcome of oocyte donation cycles, Molecular control of the implantation window, Interpretation of plasma luteinizing hormone assay for the collection of mature oocytes from women: definition of a luteinizing hormone surge-initiating rise, Live birth after blastocyst transfer following only 2 days of progesterone administration in an agonadal oocyte recipient, Pregnancy loss after frozen-embryo transfer--a comparison of three protocols, A Phase III randomized controlled trial comparing the efficacy, safety and tolerability of oral dydrogesterone versus micronized vaginal progesterone for luteal support in in vitro fertilization, Vitrified-warmed blastocyst transfer on the 5th or 7th day of progesterone supplementation in an artificial cycle: a randomised controlled trial. If the results are low, it i Read More  Givens CR, Markun LC, Ryan IP, Chenette PE, Herbert CM, Schriock ED. Though some studies have reported increased D14 TSH after fresh ET, few studies have focused on the impact of D14 TSH after frozen-thawed embryo transfer (FET) on clinical outcomes, the ideal D14 TSH after FET, whether this parameter matters for clinical outcomes.
 If you were planning a fresh embryo transfer, your provider will likely cancel the transfer and freeze all of your embryos. Below are typical serum levels of estradiol you might expect in the early follicular phase of your menstrual cycle (before you start the stimulation) and during the treatment cycle. One large retrospective study of over 900 IVF cycles examined the rate of estrogen increases in women with varying ovarian reserve levels.
 . Oxford University Press is a department of the University of Oxford. On the other hand, transferring Day 4 embryos on the third day of progesterone supplementation (a time being equivalent to 2 days after OR) was also deleterious (van de Vijver et al., 2016). Women undergoing IVF who have high levels of the hormone progesterone when their egg cells are retrieved benefit from having the resulting embryos frozen and transferred back to the uterus at a later date, the researchers found. %%EOF
Estradiol levels are essential for monitoring the progress of your in vitro fertilization cycle. Alternatively our testing kits are a great way of discovering hormone health related issues at home.
 Glujovsky D, Pesce R, Fiszbajn G, Sueldo C, Hart RJ, Ciapponi A. Gomaa H, Casper RF, Esfandiari N, Bentov Y. Griesinger G, Weig M, Schroer A, Diedrich K, Kolibianakis EM. As individual timing of the WOI becomes increasingly substantiated by diagnostics tools, subsequent time corrections might offer further opportunities to increase FET success rates.
Some of the most common serious side effects include: While the above list may be a source of concern, if you suspect you are living with estrogen dominance, the most important thing is to get screened before letting worry take over. and C.B. Low estrogen is associated with decreased success rates, primarily due to the fact that fewer eggs are collected, and thus fewer embryos are generated. . Conversely, given that a previous meta-analysis has associated endometrial thickness 7 mm in fresh IVF cycles with a lower chance of pregnancy, this cut-off value is generally extrapolated to FET as well; however, the actual value of this arbitrary cut-off and whether the same limit can be extrapolated to frozen cycles requires further research (Dain et al., 2013; Kasius et al., 2014). WebSummary. Most clinics do not measure estrogen. If you have two follicles growing, your estradiol level might be between 300-600 pg/mL at its peak. C.B. No studies have investigated whether the timing of FET should be different for embryos cryopreserved by slow-freezing or vitrification. WebFor anyone who's done a frozen embryo transfer (FET), what tests, supplements etc would you highly recommend to increase the odds of a successful FET? These conditions are serious, however, the good news is that their development is slow so if you are vigilant and take action when you notice the early signs of estrogen dominance then you can reduce the chances of these conditions developing. However, the universal application of HRT cycles may have potential disadvantages including an increased cost, inconvenience and the potential adverse events associated with estrogen supplementation (e.g. Three retrospective studies comparing true versus modified NC failed to demonstrate significant differences in clinical outcomes (Weissman et al., 2009; Chang et al., 2011; Toms et al., 2012), however a recent large retrospective analysis did show a significant difference in clinical pregnancy rate (CPR) in favor of the true NC FET (without LPS) versus the modified NC FET (with LPS) even after adapting the transfer policy to the type of ovulation trigger and excluding patients that administered hCG despite a LH surge (46.9% versus 29.7%, P < 0.001) (Montagut et al., 2016). Specifically, late-follicular serum estradiol and luteinizing hormone (LH) do not seem to predict outcome (Remohi et al., 1997; Banz et al., 2002; Griesinger et al., 2007; Niu et al., 2008; Bocca et al., 2015). 5 Side Effects Using estradiol for more than a year Introduction. It furthers the University's objective of excellence in research, scholarship, and education by publishing worldwide, This PDF is available to Subscribers Only. Things that can elevate a Day 3 estradiol include: If you intend to start an IVF cycle and your estrogen levels are elevated, we generally will delay starting until we get the values back to a normal range. Conversely, a study conducted in oocyte recipients showed a higher biochemical pregnancy rate when progesterone supplementation was longer (i.e. Decidualization, the secretory transformation that the endometrial stromal compartment undergoes to accommodate pregnancy, plays an important role in receptivity as it is thought to contribute to the active selection of embryos attempting implantation (Brosens et al., 2014). Unexpected dropping estrogen levels: Some IVF protocols do have an expected drop in estrogen prior to the egg retrieval stage. Literature on the topic was retrieved in PubMed and references from relevant articles were investigated until June 2017. For employers, housing facilities, payers, providers, and government. H.T. WebHigh serum E2 values have indeed been associated with poorer outcome by others as well, however, they report mainly a higher risk for low birth weight/being small for gestational Specific attention is warranted in situations where embryo thawing is followed by further in vitro culture and embryonic development prior to transfer. Our objective was to characterize estrogen receptor 1 (ESR1) in human and mouse embryos and determine the effect of estradiol (E2) supplementation on pre- and peri-implantation blastocyst At the basic research level, the evidence points toward the NC being superior to HRT. Low estradiol responses in oocyte donors undergoing gonadotropin stimulation do not influence clinical outcomes. The goal of fertility-sparing treatment (FST) for patients desiring future fertility with EMCA, and its precursor EH, is to clear the affected tissue and revert to normal endometrial function. Third, some women from the modified NC group in this same study already had an LH rise on the day of hCG administration which was associated with significantly lower pregnancy rates (suspected to be because of higher grade of embryo-endometrial asynchrony), while serum progesterone >1 ng/ml was an exclusion criterion in the study by Weissman et al. In order to promote favorable conditions for implantation before frozenthawed embryo transfer (FET), various options ranging from reliance on the natural cycle, to ovarian stimulation or artificial endometrial preparation (AEP) (i.e. and H.T. The actual level can range from as low as 20 pg/mL to as high as >100 pg/mL on Day 3. See also: Signs Of High Estrogen In Women. A significant difference in live birth rate was found below and above the median progesterone level (10.9 ng/ml, p = 0.007). tOR, theoretical oocyte retrieval, P, progesterone. WebIn frozen embryo transfer cycles, estrogen can be used to help thicken the lining of the uterus and prepare it for pregnancy. If you do not ovulate, there is no empty follicle for progesterone production. A recent RCT compared the outcomes of blastocyst transfer with either 5 or 7 days of progesterone supplementation and CPRs once more tended to be in favor of the shorter protocol, although not statistically significant (32.5% versus 27.6%) (van de Vijver et al., 2017).
 Banz C, Katalinic A, Al-Hasani S, Seelig AS, Weiss JM, Diedrich K, Ludwig M. Belva F, Bonduelle M, Roelants M, Verheyen G, Van Landuyt L. Belva F, Henriet S, Van den Abbeel E, Camus M, Devroey P, Van der Elst J, Liebaers I, Haentjens P, Bonduelle M. Ben-Meir A, Aboo-Dia M, Revel A, Eizenman E, Laufer N, Simon A. Bjuresten K, Landgren B-M, Hovatta O, Stavreus-Evers A. Blockeel C, Drakopoulos P, Santos-Ribeiro S, Polyzos NP, Tournaye H. Bocca S, Bondia Real E, Lynch S, Stadtmauer L, Beydoun H, Mayer J, Oehninger S. Borini A, Dal Prato L, Bianchi L, Violini F, Cattoli M, Flamigni C. Bosch E, Labarta E, Crespo J, Simn C, Remoh J, Jenkins J, Pellicer A. Bourgain C, Devroey P, Van Waesberghe L, Smitz J, Van Steirteghem AC. Easy testing for 2 often symptomless STDs, Covers the same 5 STDs as tested for by physicians, Have complete peace of mind by testing for 8 STDs, For individuals collecting their samples in their own homes. In males, they can cause breast tissue 197 0 obj
<>
endobj
Endometrial Receptivity Array, ERA, Igenomix) (Daz-Gimeno et al., 2011), the use of a standardized nomenclature is of utmost importance. If you are concerend about your hormone health, taking a test or consulting a medical expert are sure ways of identifying issues. The reason is that high estrogen levels can lead to the development of ovarian hyperstimulation syndrome (OHSS), which is a potentially serious condition following IVF treatment.
 Interestingly, when compared to HRT, gonadotropins or letrozole ovarian stimulation did seem to have a slightly increased chance for live birth. is funded by the Research Fund of Flanders (FWO). Acosta AA, Elberger L, Borghi M, Calamera JC, Chemes H, Doncel GF, Kliman H, Lema B, Lustig L, Papier S. Alsbjerg B, Polyzos NP, Elbaek HO, Povlsen BB, Andersen CY, Humaidan P. Altme S, Tamm-Rosenstein K, Esteban FJ, Simm J, Kolberg L, Peterson H, Metsis M, Haldre K, Horcajadas JA, Salumets A et al. Published by Oxford University Press on behalf of the European Society of Human Reproduction and Embryology.

Remohi J, Ardiles G, Garcia-Velasco JA, Gaitan P, Simon C, Pellicer A. Roque M, Lattes K, Serra S, Sol I, Geber S, Carreras R, Checa MA. For those who need a fit-to-fly PCR or TMA travel certificate. These anovulatory cycles are most common among women between the ages of 30 and 50 and in women with secondary conditions which affect ovulation, such as polycystic ovary syndrome and endometriosis. Another retrospective study investigating true NC FET LPS by two IM injections of hCG (the day of FET and 6 days later) failed to show any difference in outcome (Lee et al., 2013). Hreinsson J, Hardarson T, Lind A-K, Nilsson S, Westlander G. Ishihara O, Araki R, Kuwahara A, Itakura A, Saito H, Adamson GD. WebFour days after embryo transfer the estrogen level is 950. is this normal? Hormonal imbalances including estrogen dominance are often responsible for fertility issues couples may face when trying to get pregnant. However, there is no RCT comparing IM and vaginal routes in HRT FET cycles. Retrospective data are conflicting, being in favor of the IM route (Haddad et al., 2007; Kaser et al., 2012) or showing no significant differences in terms of outcome (Shapiro et al., 2014). The synchronous interaction between a competent embryo and a receptive endometrium is a complex molecular process indispensable for successful implantation (Tabibzadeh, 1998). On the contrary, if you develop high estrogen levels in your cycle, be sure to follow closely with your fertility doctor to discuss OHSS risk mitigation. All content and information on this website are for informational and educational purposes only. Your email address will not be published. A meta-analysis concluded that the type of estrogen supplementation and route of administration had no effect on the success rates of FETs (Glujovsky et al., 2010). Caution, however, is warranted, given that a higher miscarriage rate with shorter estrogen supplementation has also been previously reported (Borini et al., 2001). When using urinary LH measurement, this difference in timing might not be beneficial, since a 1-day delay for the detection of peak hormone levels in the urine has been described (Cekan et al., 1986). Lutjen P, Trounson A, Leeton J, Findlay J, Wood C, Renou P. Merriam KS, Leake KA, Elliot M, Matthews ML, Usadi RS, Hurst BS. Soares SR, Troncoso C, Bosch E, Serra V, Simn C, Remoh J, Pellicer A. Testart J, Frydman R, Feinstein MC, Thebault A, Roger M, Scholler R. Toms C, Alsbjerg B, Martikainen H, Humaidan P. Tournaye H, Sukhikh GT, Kahler E, Griesinger G. van de Vijver A, Drakopoulos P, Polyzos NP, Van Landuyt L, Mackens S, Santos-Ribeiro S, Vloeberghs V, Tournaye H, Blockeel C. van de Vijver A, Polyzos NP, Van Landuyt L, De Vos M, Camus M, Stoop D, Tournaye H, Blockeel C. van de Vijver A, Polyzos NP, Van Landuyt L, Mackens S, Stoop D, Camus M, De Vos M, Tournaye H, Blockeel C. Veleva Z, Tiitinen A, Vilska S, Hydn-Granskog C, Toms C, Martikainen H, Tapanainen JS. (;G\? Another hypothesis is that, due to a later timing of the WOI, delayed embryos may have a higher chance of encountering a receptive endometrium, allowing them to implant but then being at increased risk for early pregnancy loss.
All rights reserved. However, until well-designed prospective studies are performed, no definitive recommendation on the use of ovarian stimulation during FET can be made. In some patients, it is necessary to maintain low estrogen levels (for example, patients with estrogen-sensitive breast cancer). . When estrogen levels are high, sperm levels may fall and lead 1). Although the serum hormone levels in such cases are often exhaustively assessed (Casper et al., 2016), the role of such endocrine monitoring in addition to the usual ultrasound monitoring is a subject of much debate in both true and modified NC FETs (Groenewoud et al., 2012, 2017; Lee et al., 2014). Regarding progesterone supplementation itself, there is little agreement on the ideal route of administration and dose. Groenewoud ER, Cantineau AEP, Kollen BJ, Macklon NS, Cohlen BJ. This is a more common practice for logistical reasons and because this method is more likely to result in a live birth.  After the egg is released, its empty follicle becomes a factory for progesterone production until the egg is either fertilized and implants in your uterus or your period begins. Webhigh estrogen level during an IVF cycle; high doses of hCG during any given IVF cycle; low body mass index (BMI) Related: 5 things to do and 3 things to avoid after your El-Toukhy T, Coomarasamy A, Khairy M, Sunkara K, Seed P, Khalaf Y, Braude P. El-Toukhy T, Taylor A, Khalaf Y, Al-Darazi K, Rowell P, Seed P, Braude P. Escrib M-J, Bellver J, Bosch E, Snchez M, Pellicer A, Remoh J. European IVF-Monitoring Consortium (EIM), European Society of Human Reproduction and Embryology (ESHRE), Kupka MS, DHooghe T, Ferraretti AP, de Mouzon J, Erb K, Castilla JA, Calhaz-Jorge C, De Geyter C, Goossens V. Evans J, Hannan NJ, Edgell TA, Vollenhoven BJ, Lutjen PJ, Osianlis T, Salamonsen LA, Rombauts LJF. Our retrospective analysis (Montagut et al., 2016) did not show a significant difference in CPR when comparing true NC FET with or without MVP; on the contrary, there was a trend favouring one not to supplement (CPR 46.9% versus 39.9%). Groenewoud ER, Cohlen BJ, Al-Oraiby A, Brinkhuis EA, Broekmans FMJ, de Bruin JP, van den Dool G, Fleisher K, Friederich J, Goddijn M et al.